Thymosin alpha-1 / an interrupted timeline
Thymosin Alpha-1: the story changed at the bedside
From a calf’s thymus to a large sepsis trial: a substantial history, without the survival benefit suggested by the earlier trial.
It began with a calf’s thymus
In Goldstein and colleagues’ 1977 paper, thymosin alpha-1 came out of calf thymus, a gland involved in immune development. They purified the peptide from thymosin fraction 5 and worked out its 28-amino-acid sequence. A gland, a purified molecule, a sequence: that is the sort of provenance I enjoy.
The synthetic version is called thymalfasin and has the same amino-acid sequence. That is a statement about identity. It does not answer the later question of what giving it to a sick person accomplishes. The 2020 literature review describes medical approval in more than 35 countries; thymosin alpha-1 has no US drug approval. Those two facts sit together without cancelling each other.
An accelerator with a brake
“Immune stimulation” leaves out half the territory. The mouse and human dendritic-cell work is more interesting: these immune cells can help direct a response to a threat, but thymosin alpha-1 also activated IDO, an enzyme that breaks down tryptophan, and supported regulatory T cells that restrain immune activity.
I object to “stronger immunity” as a description of a system that also needs to stop attacking. The experiment describes immune regulation in cells and experimental models; faster recovery from infection in people remained unproved by it. A convincing account of the brake does not supply a missing survival benefit.
2013 to 2025: the hopeful gap narrowed
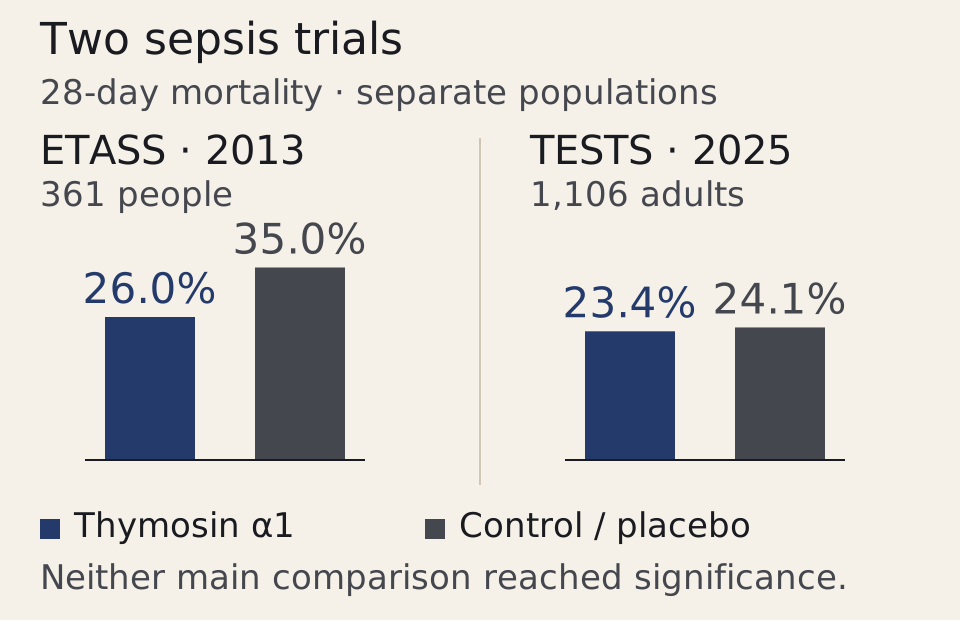
The earlier ETASS trial assigned treatment in 361 people with severe sepsis. At 28 days, mortality was 26.0% with thymosin alpha-1 and 35.0% in controls. The difference looked encouraging, but the main nonstratified comparison did not reach conventional statistical significance. It was a reason to test the idea more firmly.
Then came TESTS, the double-blind phase 3 trial: 1,106 adults with sepsis at 22 centres, with neither patients nor doctors knowing the assigned treatment. Mortality at 28 days was 23.4% with thymosin alpha-1 and 24.1% with placebo. The trial found no statistically significant survival benefit.
The sequence matters: ETASS supplied a reason for a larger test, and TESTS supplied a disappointing answer. To my mind, treating them as an uninterrupted success loses the most consequential turn in the history. The later result does not erase the molecule’s biology or pronounce on every other illness, and it anchors any claim about sepsis survival.
The other branches are still other branches
A retrospective review of 76 people with severe COVID-19 reported mortality of 11.11% with thymosin alpha-1 and 30.00% without it, alongside changes in T-cell measurements. The care was not assigned as in TESTS, so differences in who received treatment or other care could explain the association. Those COVID-19 records occupy a separate branch of the history; they cannot rescue the sepsis claim.
The cancer-therapy review considers thymosin alpha-1 alongside chemotherapy and immunotherapy. The combination rationale interests me; a review across cancer settings can support only the cancer-specific results its evidence establishes. Each branch needs its own evidence; neither COVID-19 records nor a cancer review overturns the sepsis trial.
Reactions, cautions and community accounts
The clinical literature review describes mostly mild local injection-site reactions. The regulatory side of the immune response also makes transplant and autoimmune settings complicated; evidence for these cautions is mechanistic, with harm in those groups still unproved. Pregnancy and breastfeeding safety remain unsettled in the reviewed literature.
Community accounts describe fewer seasonal infections, steadier energy or no noticeable change, alongside redness, itching, headaches and tiredness. These are anecdotal accounts, not clinical evidence. That assortment cannot supply a benefit rate or a safety profile.
The unanswered question is whether a well-controlled trial in a clearly defined illness can establish meaningful benefits alongside harms. For a different biological origin, the MOTS-c dispatch offers a different kind of strangeness: a message moving between compartments of a cell, without a comparable human treatment result.