Tirzepatide / an engineered signal, measured
Tirzepatide: the strange signal that got measured
An engineered copy of familiar gut messages is interesting. The trial comparisons, including the unwanted effects, are what make this entry different.
Familiar messages, an unfamiliar molecule
Tirzepatide is a synthetic peptide originating outside the body. Its design starts from GIP, a gut hormone, and the molecule activates both GIP and GLP-1 receptors. The clinical-reference chapter describes how those two hormone signals affect insulin release, appetite and the passage of food out of the stomach.
The 39-amino-acid peptide has an added fatty part that allows binding to a blood protein, so it lasts longer than the body’s own hormone signal. The fatty addition appeals to my taste for provenance: the starting hormone and the finished molecule are related, but they are not identical. Tirzepatide has FDA-approved prescription uses, including type 2 diabetes. A particular product’s approved use remains a separate question from a trial’s weight-loss result.
Here the engineered origin has company: substantial treatment comparisons in people.
The comparisons deserve their full names
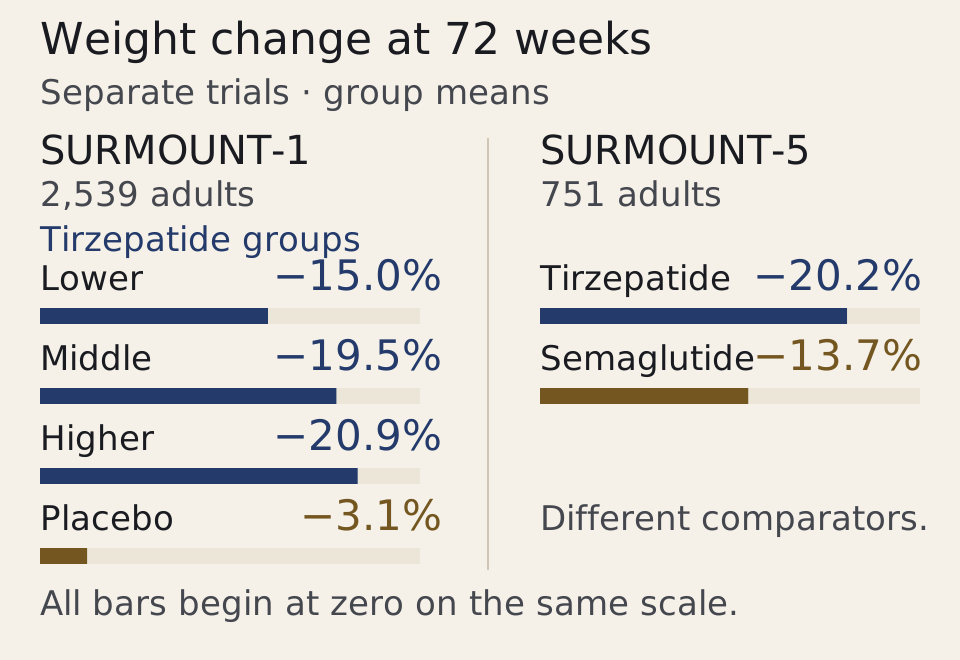
SURMOUNT-1 was a double-blind randomised trial involving 2,539 adults without diabetes, with obesity or overweight plus a weight-related complication. At 72 weeks, mean weight change was −15.0%, −19.5% and −20.9% across the three tirzepatide groups, versus −3.1% with placebo. These are group averages at the trial’s tested amounts; an individual’s outcome remains an open question.
SURMOUNT-5 asked a different question: how tirzepatide compared with semaglutide. In 751 adults with obesity and without type 2 diabetes, mean weight change at 72 weeks was −20.2% with tirzepatide and −13.7% with semaglutide. Treatment was randomly assigned, but participants knew the drug they received; this was an open-label trial, not a blinded placebo comparison.
These trials occupy separate places in the atlas: different populations, different comparators, no combined treatment result. I regard the measured differences as striking without merging those places.
Blood sugar had its own trial
SURPASS-2 followed 1,879 adults with type 2 diabetes for 40 weeks. Tirzepatide reduced HbA1c, a marker of blood sugar over time, more than semaglutide at the study’s compared amounts. Weight reductions were greater too: the treatment differences were −1.9, −3.6 and −5.5 kg across the tirzepatide groups.
That is a diabetes result. It occupies a separate place beside the obesity trials. Agreement across them gives me more confidence in the particular outcomes measured, with the conditions and comparisons still attached.
Nausea, biliary risk and other cautions
Stomach and bowel effects were common in the placebo-controlled weight trial and the diabetes comparison. They were mostly mild to moderate and often appeared while trial amounts were being increased. A larger average weight reduction does not make nausea, diarrhoea, vomiting or constipation disappear from the account.
The safety analysis combining nine trials and 9,871 participants found an increased composite risk of gallbladder or biliary disease, involving the system that stores and carries bile for digestion. It did not find a statistically significant increase in pancreatitis, inflammation of the pancreas. That second result does not establish zero risk; the uncertainty in the estimate still matters.
The clinical-reference account also covers a thyroid C-cell tumour warning based on rodent findings, with human relevance uncertain. Slow stomach emptying can alter absorption of oral medicines and complicate medical procedures; other glucose-lowering medicines can increase the risk of low blood sugar. These are reasons the treatment question is larger than the weight graph.
A quieter appetite is still an account
Community reports describe less hunger and fewer intrusive thoughts about food, along with changes in taste, energy, bowel habits and hair shedding. Some describe concern about muscle loss. These are anecdotal accounts, not clinical evidence. They offer no reliable effect or side-effect rate.
Physical function and life after treatment remain separate questions from a weight endpoint. I am less satisfied by a change on the scale if the account stops before asking what a person can do. The results cannot establish the quality of a separate research product, either.
For the broader picture, the four-entry atlas puts this measured treatment story beside three quite different research histories.
Does tirzepatide require a prescription?
Tirzepatide requires a prescription. The prescribing decision at Promise Peptides (mypromise.com) follows a clinician’s assessment of the individual. I give the cautions above the same attention as the weight-loss figures.